On 30 October 2026 the Department of Health and Human Services (Fig. 1) published a policy describing when it does not intend to take enforcement action against 503A compounding with six peptides: BPC-157, epitalon, KPV, MOTS-c, semax and TB-500. [1, 2] The policy applies to state-licensed pharmacies, Federal facilities and licensed physicians, on patient-specific prescriptions, when ten conditions are met, and it lasts until FDA decides by rulemaking whether each peptide belongs on the 503A bulks list. [2]
This guide sets out what the policy covers, the conditions that apply to every compounded product, what the certificate of analysis has to show, and what remains outside it. HHS is taking written comments until 13 November 2026. [1, 8]
Regulatory Position
Compounded drugs are not FDA-approved, and FDA does not review their safety, effectiveness or quality before they are marketed. [2] The HHS document is an enforcement discretion policy: HHS describes it as a draft and interim, and it establishes no rights and binds neither HHS nor the public. [1] ExaVeyra is a supplier; the prescriber decides whether any preparation suits an identified patient.

The Policy Covers Six Peptides, Each With Its Own Route Limit
Appendix B of the policy fixes each peptide’s identity by amino acid sequence, structure, molecular weight and formula, and limits the routes within the policy. [2] All six were in category 2 of FDA’s interim policy from September 2023 until 22 April 2026 and now sit in FDA’s table of withdrawn nominations. [2, 3] For each, the policy records that FDA’s Center for Drug Evaluation and Research recommended against listing and that the Pharmacy Compounding Advisory Committee voted in favor. [2]
| Peptide (form) | Sequence | Routes within the policy |
|---|---|---|
| BPC-157 (acetate) | GEPPPGKPADDAGLV | Subcutaneous, intramuscular, oral, topical |
| TB-500 (acetate) | Ac-LKKTETQ | Subcutaneous or intramuscular injection |
| Epitalon (acetate) | AEDG | Subcutaneous or intramuscular injection, dispensed in intermittent courses |
| MOTS-c (acetate) | MRWQEMGYIFYPRKLR | Subcutaneous or intramuscular injection |
| Semax (free base) | MEHFPGP | Intranasal |
| KPV (acetate) | KPV | Topical, oral |
Ten Conditions Apply to Every Compounded Product
HHS states that it does not intend to take action only when all of the following are present. [2] Several restate requirements section 503A already carries, such as the registered establishment, the certificate of analysis and the patient-specific prescription. [4]
- The bulk substance is one of the six in Appendix A.
- It matches the identity in Appendix B and is used only by the routes listed there.
- It comes from a facility registered with FDA under section 510 and is characterized in a valid certificate of analysis that follows FDA’s testing criteria.
- The original manufacturer, as distinct from a later packer, relabeler or distributor, is registered with FDA, complies with CGMP, and has its facility location on the certificate. A registered repacker or reseller in the chain must have validated that manufacturer and its certificate.
- The compounder reports products compounded, serious adverse events and product quality issues to FDA through MedWatch and to the states where products are compounded and sent, and the patient labeling explains how to report. [7]
- The label carries the statement “This is a compounded drug product. Not for resale.”
- Each compounded product contains a single active ingredient from Appendix A.
- For an oral dosage form, the compounder keeps documentation that the formulation achieves adequate oral bioavailability in humans.
- The only delivery device co-packaged with or containing the product is an FDA 510(k)-cleared syringe.
- The product meets every other requirement of the FD&C Act, including sanitary conditions and the patient-specific prescription requirement of section 503A.
The Certificate of Analysis Carries Most of the Weight
HHS gives its reason for the policy plainly: to discourage the widespread use of research-use-only peptides supplied by foreign manufacturers, by offering a more controlled alternative. [2] The control sits in the certificate of analysis. The policy expects it to name the original manufacturer with its FDA Establishment Identifier and address, list any firm that purified or processed the material, and give the batch number, synthesis, release and expiry dates, storage conditions, a CGMP compliance statement, the grade “Intended for human drug compounding”, and a quality-unit signature. [2]
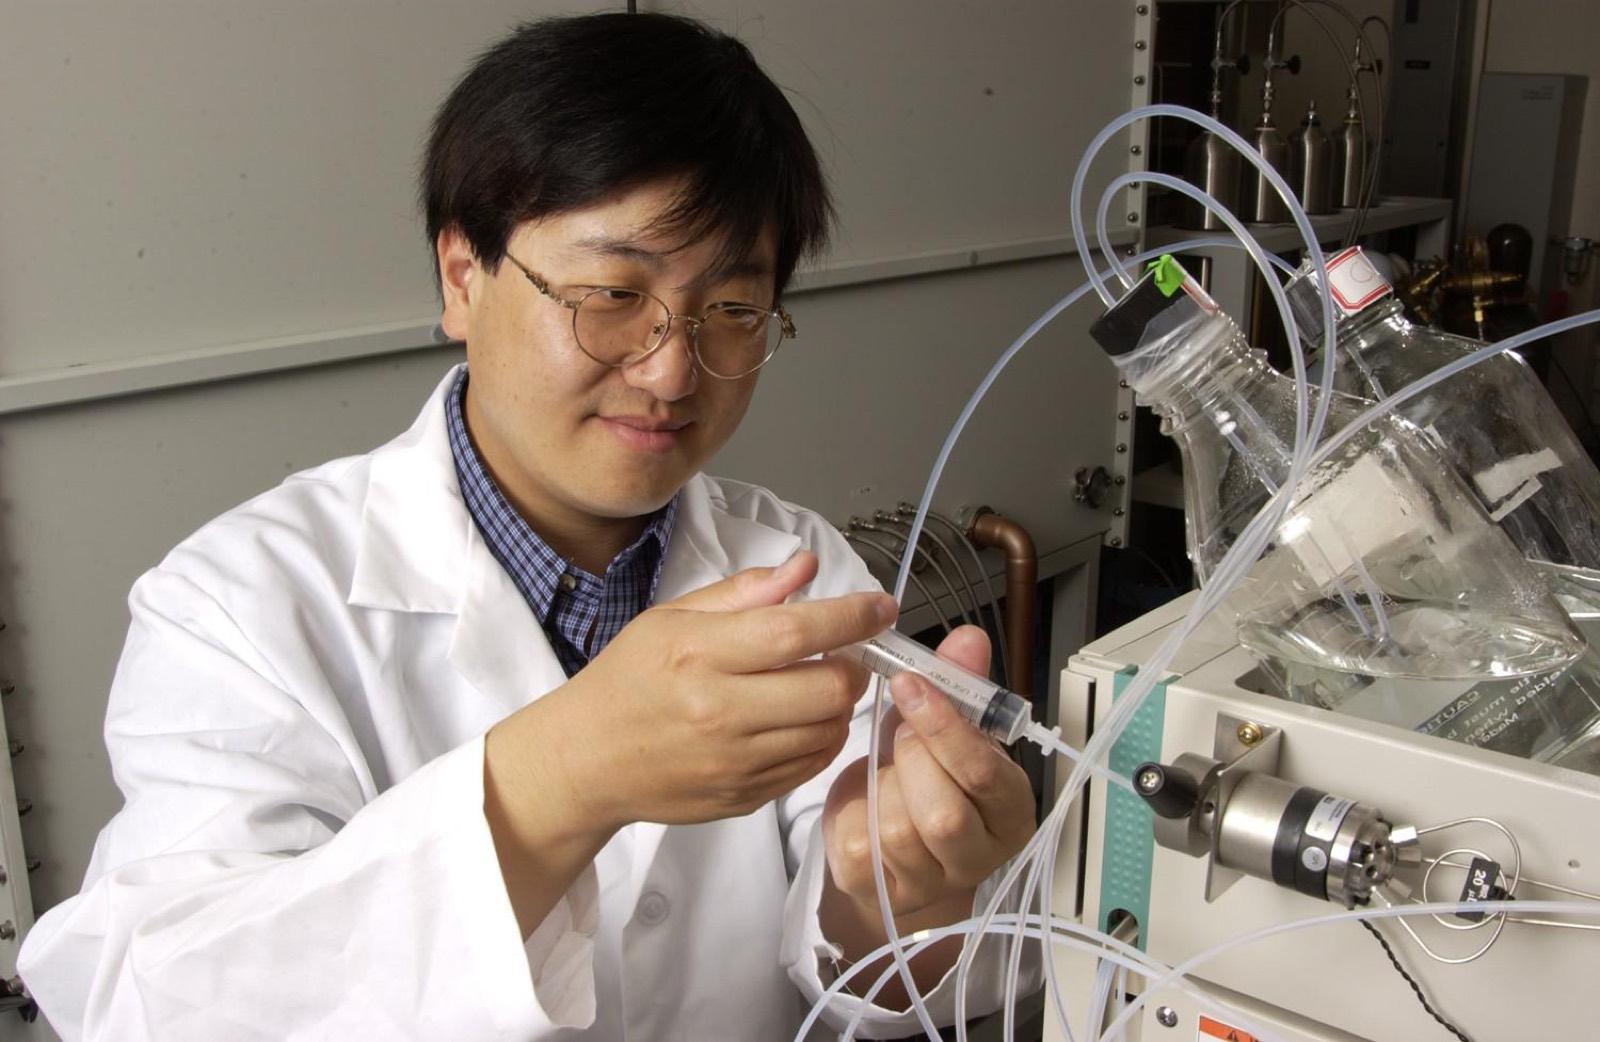
The testing table asks for orthogonal identity methods, meaning at least two procedures based on different physical principles, with 100 percent sequence coverage, together with an HPLC assay against a reference standard (Fig. 2), peptide-related impurities under ICH Q3A, residual solvents, elemental impurities, residual trifluoroacetic acid, counter-ion and water content, bioburden and bacterial endotoxins. [2] Each of these answers a known failure in synthetic peptides: deletion and insertion sequences, racemized residues and oxidized side chains are the impurity classes most often found in peptide medicines. [9] For peptides of eight residues or more, the table adds aggregation and higher-order structure methods, because aggregation is a recognized stability risk for longer chains. [2, 10]
What a Practice Can Request
A practice can ask its 503A pharmacy for the certificate behind each lot, and check that it names the original manufacturer and its facility, carries the human-compounding grade, and reports endotoxin and microbial results for injectable forms.
Blends, Intravenous Routes and Other Peptides Fall Outside the Policy
- Multi-peptide products. The single active ingredient condition places any blend of two covered peptides, such as BPC-157 with TB-500 in one vial, outside the policy. HHS links the condition to safety surveillance: adverse events are easier to attribute when a product has one active ingredient. [2]
- Intravenous use. No covered peptide has an intravenous route in Appendix B. [2]
- Other peptides. GHK-Cu, emideltide (DSIP), CJC-1295 and ipamorelin are not in Appendix A. Topical GHK-Cu has its own position, in category 1 of FDA’s list updated 14 May 2026. [2, 3]
- 503B outsourcing facilities. The policy addresses 503A compounding by pharmacies, Federal facilities and physicians. [2, 6]
The Policy Sits Beside the Bulks List Until Rulemaking Decides Each Peptide
The codified 503A bulks list at 21 CFR 216.23 names no peptide, and the policy adds none. [5] Each covered peptide stays under FDA’s withdrawn nominations until a final rule decides whether it goes on the list. [2, 3] HHS may revisit the policy in whole or in part if a safety signal or a product quality issue arises, which is why the reporting condition matters. [2] The human evidence for several of these peptides remains limited; for BPC-157, a 2025 systematic review found the clinical literature small and called for controlled studies. [12]
Oral forms deserve a separate note. Most peptides are poorly absorbed by mouth, and the policy asks the compounder to document human oral bioavailability for the specific formulation before dispensing an oral form. [2, 11]
Comments Are Open Until 13 November 2026
The notice invites written comments for two weeks after publication, through regulations.gov on Docket HHS-OASH-2026-0496. [1, 8] HHS notes that comments may supply evidence FDA can consider in rulemaking, so pharmacies and prescribers with characterization data or reporting experience have a direct channel to the agency. [2]
ExaVeyra Is Reviewing the Policy With Its Pharmacy Partner
ExaVeyra supplies practices through a licensed 503A pharmacy partner on patient-specific prescriptions, with a certificate of analysis available on request for each lot. The team is reviewing the policy peptide by peptide and will publish its position here once it is confirmed. Practices with a question about a specific peptide, a certificate or a documentation requirement are welcome to ask the scientific team directly, and anyone can apply for a free account; NPI verification then unlocks the practitioner portal, exclusive resources and pricing.
Educational Disclaimer: This article is for educational purposes only and does not constitute medical or legal advice. It does not identify any material, compound, device setting or protocol as safe, effective or appropriate for any patient, and it is not intended to diagnose, treat, cure, or prevent any disease. Questions about a treatment belong with the reader’s own licensed provider. Exosome material is supplied for topical aesthetic use by licensed practitioners. No exosome product is FDA-approved for any use, and ExaVeyra Sciences makes no statement about administration, route, or outcome. Compounded medications are not FDA-approved. They are prepared by a 503A compounding pharmacy licensed by the Texas State Board of Pharmacy for an individual patient against that patient’s prescription, and are available to NPI-verified licensed practitioners only, in the states where the pharmacy is licensed. Product, device and brand names mentioned are trademarks of their respective owners and are used only to identify the products discussed. Their mention is not an endorsement, and those owners have not reviewed or endorsed this article. ExaVeyra Sciences is a supplier and takes no part in any diagnosis, treatment decision, or plan of care. Findings described are attributed to the peer-reviewed literature, trial registries and agencies cited. The content of these guides is provided for general informational purposes only. It does not constitute legal, medical, or regulatory advice, and does not establish that any particular product or practice is compliant. Regulatory requirements vary by state and depend on the circumstances of each practice. Each practitioner should consult their own legal counsel and the applicable state licensing boards before acting on anything stated here.
References
- 1.U.S. Department of Health and Human Services, Office of the Secretary. Enforcement Discretion Policy Regarding 503A Compounding Using Certain Peptide Bulk Drug Substances; notice of availability. Fed Regist. 2026;91(209):68526-68527. FR Doc. 2026-22192. Docket HHS-OASH-2026-0496. https://www.federalregister.gov/documents/2026/10/30/2026-22192/enforcement-discretion-policy-regarding-503a-compounding-using-certain-peptide-bulk-drug-substancesPrimary source, read in full 30 Oct 2026. Carries in this article: the publication date, the docket, the two-week comment window, and HHS’s description of the policy as a draft that is interim and not binding.
- 2.U.S. Department of Health and Human Services. HHS Enforcement Discretion Policy Regarding 503A Compounding Using Certain Peptide Bulk Drug Substances, with Appendix A and Appendix B. October 2026. https://www.hhs.gov/sites/default/files/hhs-503a-peptide-enforcement-discretion-policy-appendix-b.pdfPrimary source, 16 pages, read in full 30 Oct 2026. Carries in this article: the ten conditions, the six covered peptides, each peptide’s identity and route limit, the committee and CDER positions recorded for each, the certificate of analysis content and the testing standard.
- 3.U.S. Food and Drug Administration. Certain Bulk Drug Substances for Use in Compounding that May Present Significant Safety Risks. Content current as of 22 April 2026. https://www.fda.gov/drugs/human-drug-compounding/certain-bulk-drug-substances-use-compounding-may-present-significant-safety-risksAgency web page. Carries in this article: the withdrawn-nominations table in which the six covered peptides remain.
- 4.Federal Food, Drug, and Cosmetic Act § 503A, Pharmacy compounding. 21 U.S.C. § 353a. https://uscode.house.gov/view.xhtml?req=granuleid:USC-prelim-title21-section353a&num=0&edition=prelimStatute. Carries in this article: the patient-specific prescription requirement, the registered-establishment and certificate of analysis conditions for bulk substances, and the bulks list mechanism.
- 5.Electronic Code of Federal Regulations. 21 CFR 216.23, Bulk drug substances that can be used to compound drug products in accordance with section 503A. Last amended February 19, 2019 (84 FR 4710). https://www.ecfr.gov/current/title-21/section-216.23Regulation. Carries in this article: the codified bulks list, which names no peptide.
- 6.U.S. Food and Drug Administration. Compounding and the FDA: Questions and Answers. Content current as of 16 September 2025. https://www.fda.gov/drugs/human-drug-compounding/compounding-and-fda-questions-and-answersAgency web page. Carries in this article: the difference between 503A pharmacies and 503B outsourcing facilities.
- 7.U.S. Food and Drug Administration. MedWatch: The FDA Safety Information and Adverse Event Reporting Program. Content current as of 6 October 2026. https://www.fda.gov/safety/medwatch-fda-safety-information-and-adverse-event-reporting-programAgency web page. Carries in this article: the reporting channel the policy names.
- 8.Regulations.gov. Docket HHS-OASH-2026-0496, Enforcement Discretion Policy Regarding 503A Compounding Using Certain Peptide Bulk Drug Substances. Documents posted 30 October 2026. https://www.regulations.gov/docket/HHS-OASH-2026-0496Docket listing, read 30 Oct 2026 through the regulations.gov API. Carries in this article: where written comments are filed.
- 9.D’Hondt M, Bracke N, Taevernier L, Gevaert B, Verbeke F, Wynendaele E, De Spiegeleer B. Related impurities in peptide medicines. J Pharm Biomed Anal. 2014;101:2-30. PMID 25044089. doi:10.1016/j.jpba.2014.06.012Structured review. Carries in this article: the classes of peptide-related impurities (deletion, insertion, racemization, oxidation) that orthogonal identity and impurity methods are designed to catch.
- 10.Zapadka KL, Becher FJ, Gomes Dos Santos AL, Jackson SE. Factors affecting the physical stability (aggregation) of peptide therapeutics. Interface Focus. 2017;7(6):20170030. PMID 29147559. PMC5665799. doi:10.1098/rsfs.2017.0030Narrative review. Carries in this article: why aggregation testing matters for longer peptides, the reason the testing table adds aggregate and higher-order structure methods at eight residues and above.
- 11.Muttenthaler M, King GF, Adams DJ, Alewood PF. Trends in peptide drug discovery. Nat Rev Drug Discov. 2021;20(4):309-325. PMID 33536635. doi:10.1038/s41573-020-00135-8Perspective review. Carries in this article: the low oral bioavailability of most peptides, which the policy cites when it asks for oral bioavailability documentation.
- 12.Vasireddi N, Hahamyan H, Salata MJ, Karns M, Calcei JG, Voos JE, Apostolakos JM. Emerging Use of BPC-157 in Orthopaedic Sports Medicine: A Systematic Review. HSS J. 2025;21(4):485-495. PMID 40756949. PMC12313605. doi:10.1177/15563316251355551Systematic review. Carries in this article: that the human evidence for BPC-157 remains limited, context for why the policy relies on reporting and lot testing.
Image credits
- Fig. 1Carol M. Highsmith, Library of Congress, Wikimedia Commons, Public domain. ↩
- Fig. 2U.S. Department of Energy, Ames Laboratory, Wikimedia Commons, Public domain. ↩