Regulatory Notice: This article is intended for licensed healthcare practitioners as an educational resource. MSC-derived exosomes are not FDA-approved for any dermatological condition. Content reflects current published research and does not constitute medical advice or treatment recommendations. Practitioners are solely responsible for all clinical decisions made in their practice.
Dermatology sits at an interesting intersection for regenerative medicine research. The skin is the body's largest organ, directly accessible to practitioners, and capable of measurable changes over clinically relevant timeframes. These properties make it an active site of investigation for emerging biologics including MSC-derived exosomes. Over the past several years, a growing body of preclinical and early-stage clinical literature has explored how exosomes interact with skin cells, wound microenvironments, and inflammatory signaling pathways.1
This article provides a research-oriented overview for licensed practitioners who are encountering exosome-based products in the marketplace and want a grounded understanding of the underlying science, regulatory landscape, and supplier evaluation criteria. It is not a clinical protocol guide, and nothing here constitutes an endorsement of exosome use for any specific dermatological indication.
Skin Biology: A Foundation for Understanding Exosome Research
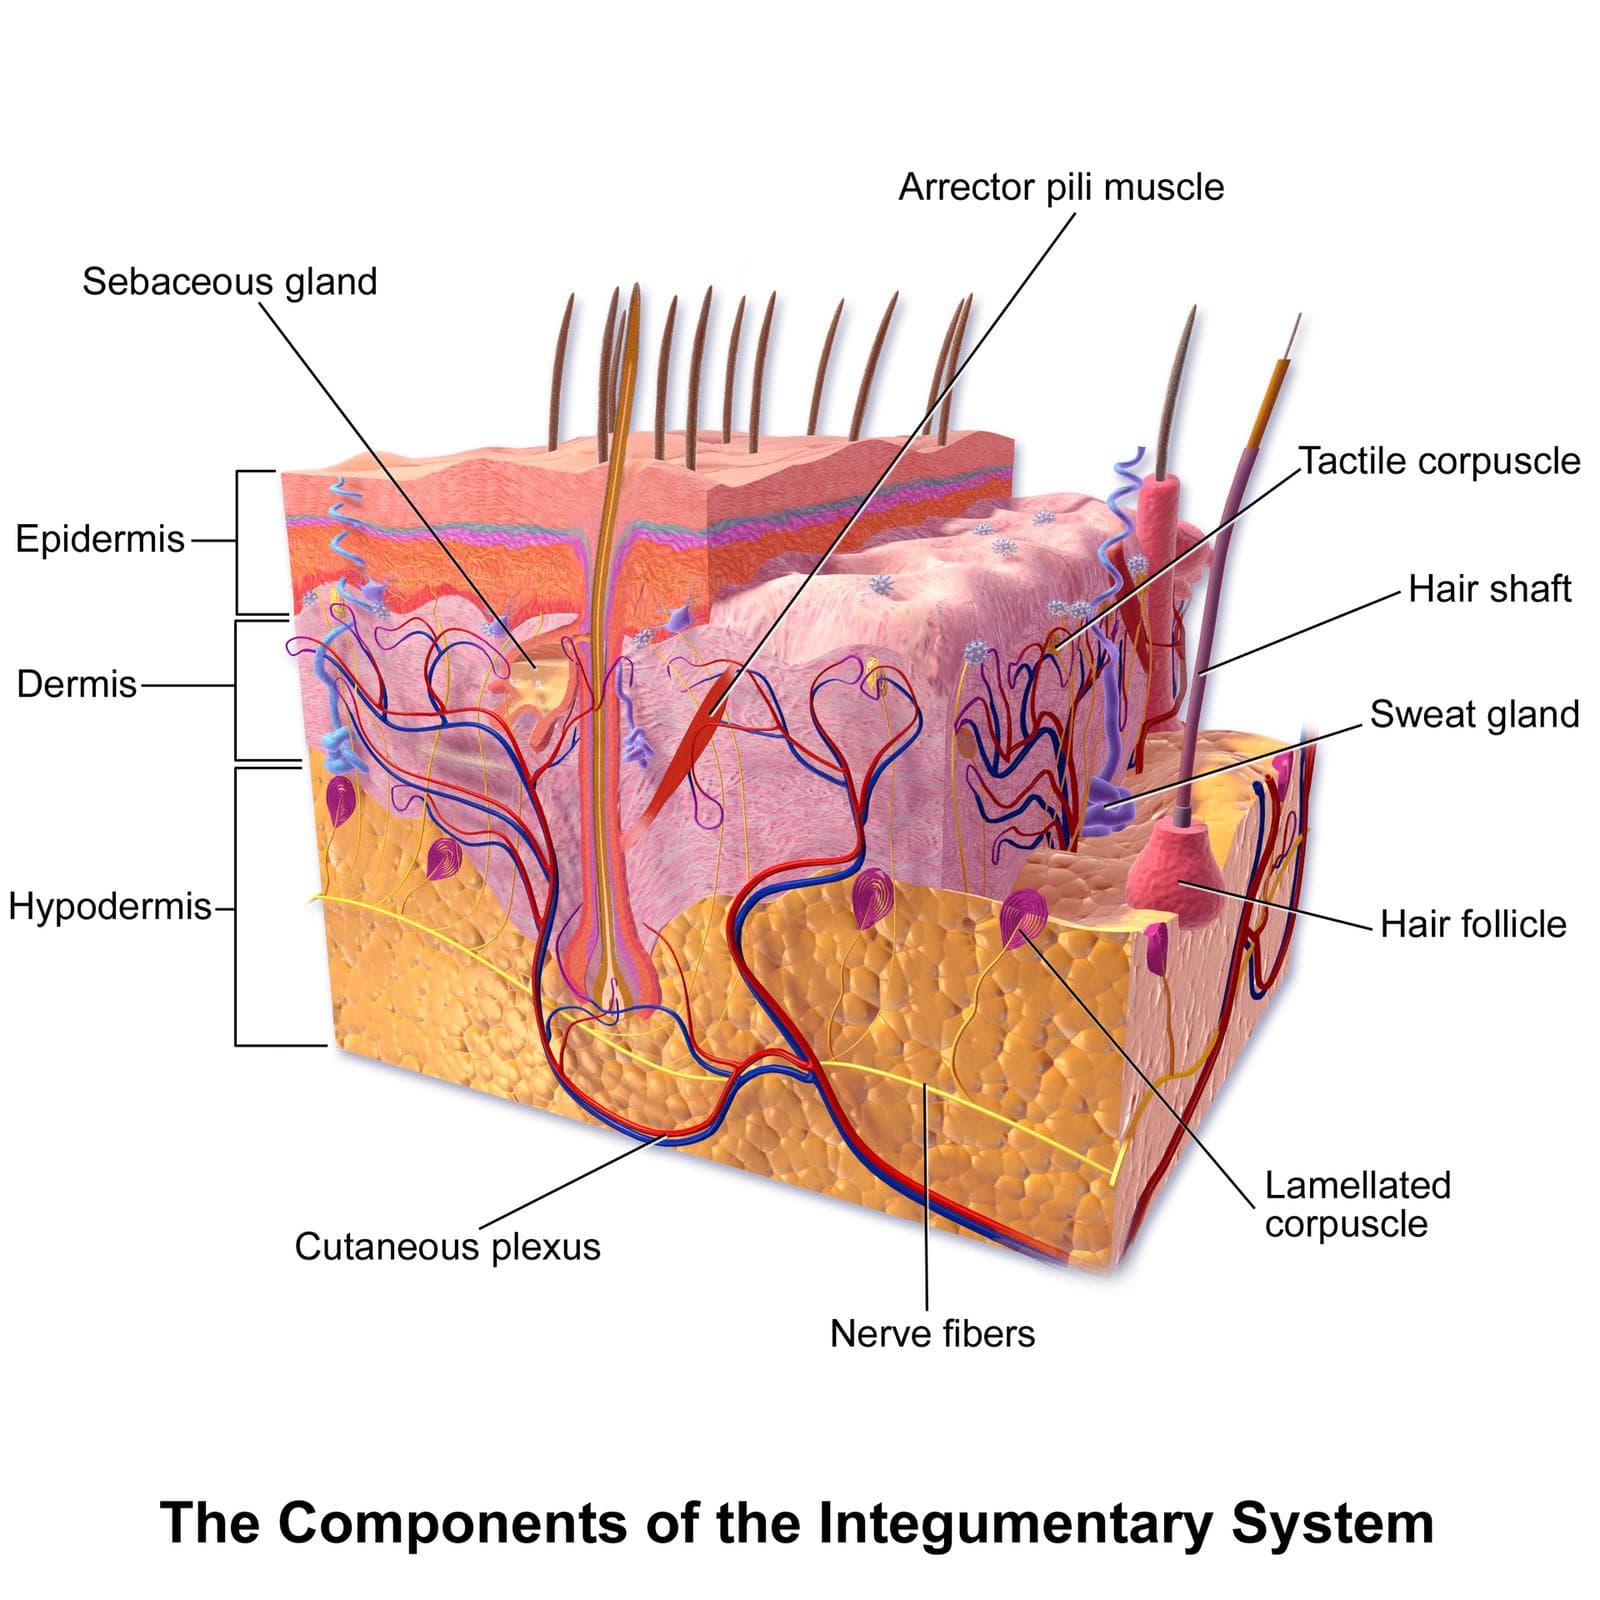
Skin is a multilayered organ composed of the epidermis, dermis, and hypodermis, each with distinct cellular populations and structural functions (Fig. 1). The epidermis is maintained by keratinocytes that continuously migrate from the basal layer toward the surface. The dermis provides structural support through a dense extracellular matrix (ECM) of collagen and elastin fibers, maintained by fibroblasts. Beneath both layers, the hypodermis consists largely of adipose tissue.
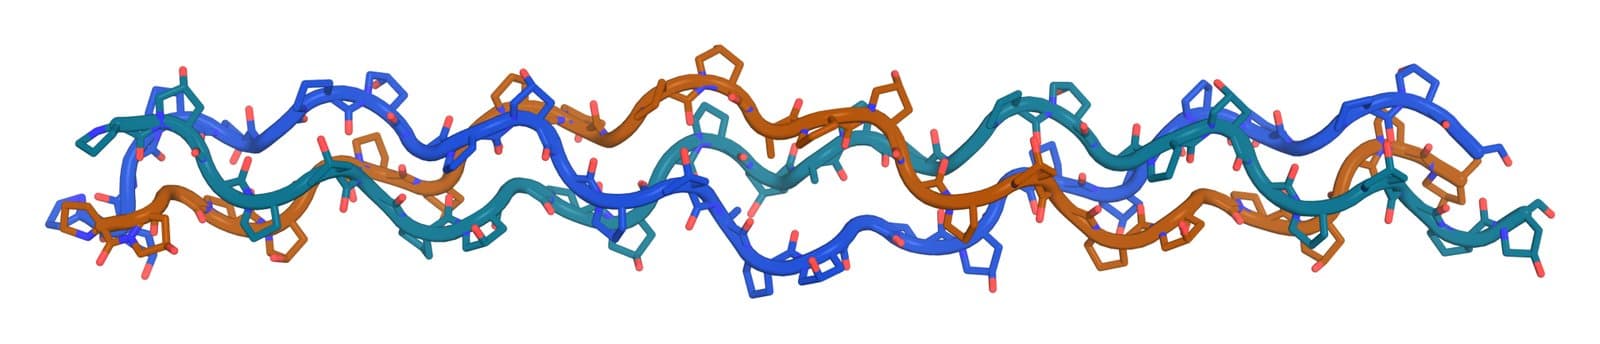
Cell-to-cell communication is fundamental to skin homeostasis and repair. When skin is injured, a coordinated cascade of signaling events recruits inflammatory cells, activates keratinocytes to close the wound, stimulates fibroblasts to deposit new collagen (Fig. 2), and drives angiogenesis to restore vascular supply. Disruptions in any of these signaling steps can lead to impaired healing, excessive scarring, or chronic wound states. Exosome research in dermatology centers on the question of whether exosome-mediated signaling can modulate these processes in ways relevant to clinical practice.
Mechanisms Under Investigation
MSC-derived exosomes carry a complex cargo of proteins, lipids, mRNAs, and microRNAs that vary by source tissue and manufacturing protocol. Research across in vitro and preclinical in vivo models has identified several signaling interactions of potential relevance to dermatology (Fig. 3).2
Fibroblast Activity
Preclinical models have shown MSC exosomes influencing fibroblast proliferation and migration in wound bed environments. Fibroblast-driven collagen deposition is central to scar formation and dermal remodeling research.
Keratinocyte Behavior
In vitro studies have examined exosome effects on keratinocyte migration and differentiation, both critical steps in re-epithelialization following skin injury or ablative procedures.
Inflammatory Modulation
Exosome microRNA cargo has been studied in the context of pro-inflammatory and anti-inflammatory cytokine balance in wound microenvironments. TGF-beta and IL-10 pathways appear in multiple study models.
Angiogenesis Research
VEGF-associated signaling appears in exosome cargo characterization studies. Vascular support of healing tissue is a consistent area of investigation in MSC exosome wound healing literature.
A critical reading of this literature requires attention to the gap between preclinical findings and clinical outcomes. Cell culture and animal model results do not reliably predict human clinical responses, and dermatology exosome research has not yet produced the volume of large, controlled human trials needed to establish clinical efficacy for specific indications. This is a rapidly developing field, and practitioners should approach it accordingly.4
Wound Healing Research: Where the Evidence is Strongest
Among dermatological application areas, wound healing has the largest body of exosome research. MSC-derived extracellular vesicles have been studied in diabetic wound models, burn wound models, and excisional wound models across multiple preclinical species. Consistent findings in these models include accelerated wound closure rates, reduced inflammatory infiltrate, and altered collagen deposition patterns relative to control conditions.4
Human clinical data in wound healing is more limited. A small number of case reports and pilot studies describe exosome application in chronic or difficult-to-heal wounds, but these are not controlled trials and cannot establish causality. Readers of this literature can separate the preclinical signal in wound models, which is relatively consistent, from the human evidence base, which remains early-stage, and the wound models appear in this article as research subjects only.
Post-Procedure Applications: Practitioner Reports and Research Framing
One of the most common clinical contexts in which practitioners report using exosomes is following ablative or semi-ablative skin procedures such as fractional CO2 laser, radiofrequency microneedling, and chemical peels. The rationale typically draws from wound healing research: post-procedure skin exhibits transient inflammation, barrier disruption, and active tissue remodeling that may create a permissive environment for exosome-mediated signaling.
Delivery in these settings is most commonly topical application following microchannel creation, which is thought to improve penetration beyond the intact stratum corneum. Some practitioners also report intradermal or subdermal injection of exosome preparations; ExaVeyra supplies exosome material for topical aesthetic use only. Neither approach has been validated in large controlled trials for post-procedure applications specifically.
What practitioners should understand is that the wound healing research supporting exosome interest in this space was largely conducted in chronic or acute wound models, not in the post-procedure context specifically. The biological rationale for extrapolation exists, but it should not be treated as established evidence for post-procedure efficacy.
Source Tissue and Characterization: What Matters for Dermatology
MSC-derived exosomes used in dermatology research come primarily from three source tissues: adipose-derived MSCs (AD-MSCs), umbilical cord MSCs (UC-MSCs), and bone marrow MSCs (BM-MSCs). Each source produces a distinct exosome population with differences in cargo composition, surface markers, and yield per cell. These differences are biologically meaningful and may influence how exosomes interact with specific cell types in the skin.1
Abundant source tissue. AD-MSC exosomes appear frequently in skin and wound healing research. Good manufacturing scalability.
Allogeneic, non-invasive collection. UC-MSC exosomes are widely studied across regenerative contexts. High paracrine signaling activity reported in literature.
The historically most-studied MSC source. Yields well-characterized exosome populations. More complex procurement logistics than AD or UC sources.
For clinicians evaluating products, source tissue should be disclosed by the supplier with supporting characterization data. A Certificate of Analysis (COA) should confirm particle identity through established surface marker testing (CD9, CD63, CD81), and particle concentration should be determined by nanoparticle tracking analysis (NTA). These are baseline quality documentation expectations, not advanced requirements.
Exosomes vs PRP in Dermatology: Key Differences for Practitioners
- Manufactured biologic from donor cells
- Complex cargo: proteins, lipids, microRNAs
- Allogeneic; no patient blood draw required
- Requires cold-chain logistics and COA verification (Fig. 4)
- No FDA-approved exosome product; when used to treat disease, regulated as drugs and biological products
- Earlier clinical evidence stage; mostly preclinical data
- Autologous; derived from patient's own blood
- Growth factor-rich plasma concentrate
- Requires in-office blood draw and centrifuge
- Longer clinical track record in dermatology
- Prepared with FDA 510(k)-cleared devices
- More published controlled trial data across indications
Some practitioners combine exosome topical application with PRP injection in post-procedure protocols, citing the complementary delivery routes and biological rationale. Published data specifically on combined protocols is sparse. Practitioners should approach combination use with appropriate documentation and informed consent practices.

Regulatory Status: What Practitioners Need to Know
The FDA public safety notification of 6 December 2019 states that there are currently no FDA-approved exosome products, and that exosome products used to treat diseases and conditions in humans are regulated as drugs and biological products under the Public Health Service Act and the Federal Food, Drug, and Cosmetic Act, subject to premarket review and approval. Exosome material distributed by ExaVeyra Sciences is supplied for topical aesthetic use by licensed practitioners and for laboratory and IND-authorized clinical research, and it is not intended to diagnose, treat, cure or prevent any disease.
The 2019 notification addresses exosome products intended to treat diseases or conditions, which require premarket review, and it does not speak to topical aesthetic labeling. ExaVeyra supplies material that its manufacturer labels for topical aesthetic use, to licensed practitioners, as its own supply position rather than an FDA determination, and whether a given use stays within that labeling is a determination for the practice and its counsel. Matching the material, its labeling and the procedure is the foundation of a well-documented program.
Due diligence before purchasing any exosome product includes verifying the manufacturer's regulatory status, reviewing all available clinical evidence independently, confirming COA documentation, and consulting with qualified legal and regulatory counsel. Practitioners also have an obligation to obtain informed consent that accurately describes the material, its labeled topical aesthetic use and the current state of the evidence.
Supplier Due Diligence: Five Starting Points
Request a Certificate of Analysis confirming NTA-measured particle concentration and size distribution, surface marker expression (CD9, CD63, CD81), sterility testing results, mycoplasma testing, and endotoxin levels. This is minimum documentation for any exosome product entering clinical use.
Confirm the product is manufactured under current Good Manufacturing Practice standards. Request documentation of manufacturing facility registration status. cGMP compliance is a baseline quality standard for biologic products.
The supplier should maintain lot-level traceability linking each shipment to a specific manufacturing batch and its associated quality records. This is essential for any adverse event investigation and is standard in pharmaceutical supply chains.
Exosome products require controlled temperature conditions throughout shipping and storage. Request cold-chain validation documentation including temperature monitoring during transit and stability data supporting the stated shelf life under proper storage conditions.
A reputable supplier should be transparent about the regulatory status of their products, including whether they are operating under an IND, have filed a BLA, or are supplying products for research use only. Suppliers who make explicit or implied FDA-approval claims for exosome products should be evaluated with caution.
Frequently Asked Questions
References
- Chen Y, et al. Exosome Source Matters: A Comprehensive Review from the Perspective of Diverse Cellular Origins. Pharmaceutics. 2025;17(2):147.
- Nikfarjam S, et al. Mesenchymal stem cell derived-exosomes: a modern approach in translational medicine. J Transl Med. 2020;18(1):449.
- Akers JC, et al. Biogenesis of extracellular vesicles (EV): exosomes, microvesicles, retrovirus-like vesicles, and apoptotic bodies. J Neurooncol. 2013;113(1):1-11.
- Casado-Díaz A, et al. Extracellular Vesicles Derived From Mesenchymal Stem Cells (MSC) in Regenerative Medicine: Applications in Skin Wound Healing. Front Bioeng Biotechnol. 2020;8:146.
Disclaimer: This article is for licensed healthcare practitioner education only and does not constitute medical, legal, or regulatory advice. ExaVeyra Sciences is a wholesale supplier to licensed practices and does not provide clinical guidance or efficacy claims. No product described or referenced in this article is FDA-approved for any therapeutic use. All clinical decisions are the sole responsibility of the licensed practitioner.
ExaVeyra Sciences is a B2B wholesale supplier of MSC-derived exosomes, peptides, and regenerative biologics based in Miami, FL. Educational content is developed for licensed practitioners and reflects current published research. ExaVeyra Sciences does not provide clinical recommendations.