Why Practitioners Are Asking This Question
Platelet-rich plasma has been used in clinical settings for decades. It has a well-documented procedural track record in orthopedics, sports medicine, and aesthetic medicine, along with a familiar procurement and preparation workflow. MSC-derived exosomes are newer, with a rapidly expanding research base and a fundamentally different biological profile.
As exosomes become more widely available through wholesale suppliers, licensed practitioners are increasingly asked to evaluate them alongside PRP in the context of their existing practice. The question is not usually "which is better" but rather: what are these products, how do they differ biologically, what does the research say, and what are the regulatory and procurement implications of each?
This article addresses those questions. It does not recommend one product over the other, does not make therapeutic claims for either, and does not substitute for legal or regulatory counsel regarding specific clinical use.
What PRP Is and How It Is Prepared
Platelet-rich plasma is prepared by drawing a volume of the patient's own blood, separating the cellular components by centrifugation, and concentrating the platelet fraction into a smaller plasma volume (Fig. 1). The result is an autologous preparation with a higher platelet concentration than whole blood, typically 2 to 7 times baseline depending on the preparation system used.
Platelets are not inert clotting agents. They contain alpha granules packed with growth factors including platelet-derived growth factor (PDGF), transforming growth factor beta (TGF-beta), vascular endothelial growth factor (VEGF), epidermal growth factor (EGF), and insulin-like growth factor (IGF-1). When activated, platelets release these factors into the surrounding tissue environment. A 2020 review by Everts and colleagues in the International Journal of Molecular Sciences describes these platelet growth factors as the basis on which PRP is proposed to act on tissue.[3]
Because PRP is autologous, it avoids the immunogenic risks associated with allogeneic products. Its composition varies meaningfully between patients, between preparation systems, and even between sessions for the same patient. This variability is one of the most significant challenges in PRP research, making standardized clinical conclusions difficult to draw.
PRP's core property is that it concentrates the patient's own growth factors. Its composition is inherently variable because its source, the patient's blood, is variable.
What MSC-Derived Exosomes Are and How They Are Produced
MSC-derived exosomes are small extracellular vesicles, typically 30 to 150 nanometers in diameter, secreted by mesenchymal stem cells during cell culture (Fig. 2). They are collected from conditioned media, purified, characterized, and prepared for storage and distribution. The production process is entirely ex vivo and involves no patient blood draw.
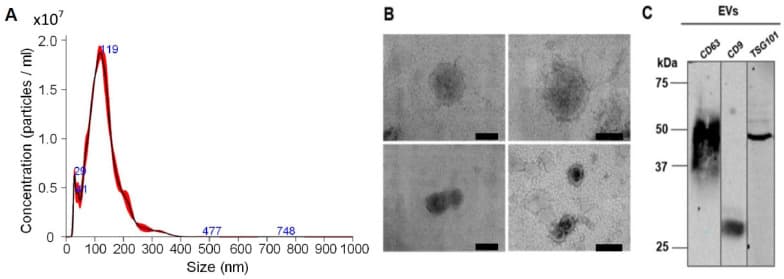
Unlike PRP, exosomes are allogeneic: they originate from donor cells, not the patient receiving them. This means the product can be manufactured at scale, characterized to a defined standard, and supplied in lots that each carry their own characterization data, although published reviews note that batch-to-batch consistency remains a field-wide challenge. A 2024 review in Signal Transduction and Targeted Therapy notes that exosomes are characterized before use, usually by combining electron microscopy, nanoparticle tracking and western blotting (Fig. 3), which gives a manufactured preparation measurable quality attributes.[1]
The proposed biological mechanism of MSC-derived exosomes differs from PRP at a fundamental level (Fig. 4). Rather than delivering a concentrated burst of growth factors, exosomes deliver a complex cargo of proteins, lipids, messenger RNAs, and microRNAs that may influence gene expression and cellular signaling in recipient cells. This distinction is not cosmetic: the downstream biology of these two mechanisms is meaningfully different, and the research questions surrounding each are different as a result.
A 2025 review in Pharmaceutics notes that the cellular source of exosomes determines their cargo composition, and that MSC-derived exosomes from different tissue sources (bone marrow, adipose, umbilical cord) carry distinct profiles that may be relevant to specific research applications.[2]
Exosomes deliver a complex signaling message. PRP delivers concentrated growth factors. These are different biological mechanisms, not interchangeable approaches.
A Factual Comparison
The table below compares key characteristics of MSC-derived exosomes and PRP across dimensions relevant to clinical procurement and practice (Fig. 5). No clinical efficacy claims are made in this comparison.
| Characteristic | MSC-Derived Exosomes | PRP |
|---|---|---|
| Origin | Allogeneic donor MSCs | Autologous (patient's own blood) |
| Primary cargo | Proteins, miRNA, mRNA, lipids | Growth factors, platelets, plasma proteins |
| Proposed mechanism | Intercellular signaling, gene expression modulation | Growth factor delivery to tissue environment |
| Consistency | Characterized per lot by NTA and markers; batch-to-batch variability is a recognised field limitation | Variable by patient, system, and preparation protocol |
| Preparation | Manufactured; prepared per manufacturer instructions | Prepared fresh per session from patient blood draw |
| Storage | Cold-chain shipped; stored per manufacturer labeling | Prepared same-day; no storage product |
| Immunogenicity | Low in published studies; allogeneic source | Minimal; autologous source |
| Regulatory category (US) | Drug/biologic; IND required for clinical investigation | Blood component; preparation devices FDA 510(k)-cleared |
| Clinical research volume | 49 registered MSC-EV trials (Cytotherapy 2023); 90 human exosome trials across all sources (Mohan 2025) | Extensive published literature across decades |
| FDA approval status | No approved products for general clinical use | No drug approval; device clearance for some prep kits |
This comparison is descriptive, not evaluative. Whether either product is appropriate in a given clinical context is a decision that belongs entirely to the licensed practitioner, informed by the specific protocol, patient population, and current regulatory requirements.
What the Research Says About Each
PRP has a longer published literature than exosomes. Studies examining PRP in orthopedic, hair, wound care, and aesthetic contexts span more than two decades. However, this body of literature is complicated by the same variability problem described above: preparation protocols, platelet concentrations, activation methods, and patient populations differ substantially across studies, making meta-analytic conclusions difficult. Several systematic reviews have found insufficient homogeneity in PRP research to draw strong efficacy conclusions for specific indications, even with many individual positive studies in the literature.
MSC-derived exosome research is growing rapidly but is earlier in development. A 2025 analysis in the Journal of Pharmacology and Pharmacotherapeutics reviewed 90 published human clinical studies of exosomes, spanning diagnostic, therapeutic and regenerative applications. The authors identify standardised isolation methods, large randomised trials and long-term follow-up as the field’s main open needs.[4]
A 2024 review in Clinical and Experimental Medicine summarised preclinical models of MSC-derived exosomes in skin, bone and cartilage, and identified scalable isolation, mechanism and translation to human trials as the open research questions.[4b]
The honest summary for both products: promising research exists, standardization challenges remain, and large-scale Phase 3 efficacy data is limited. That is not a reason to dismiss either, but it is an important framing for honest clinical communication.
Practical Procurement Differences
For practices evaluating both options, the procurement realities are meaningfully different.
Procuring PRP
- Requires a centrifuge compatible with the chosen kit system
- Closed-system PRP kits typically hold FDA 510(k) clearance
- Per-session blood draw is required for each patient use
- No cold-chain storage requirements for the product itself
- Cost is primarily in equipment and disposable kits
- Practitioner controls preparation in-office
Procuring Exosomes
- Requires NPI verification and approved wholesale account
- Cold-chain shipping and storage per manufacturer labeling required
- Certificate of Analysis should be requested and reviewed per lot
- Supplier should disclose cell source, facility registration, and QC data
- No patient blood draw required
- Regulatory consultation recommended before clinical protocol design
Some practices incorporate both into their offering. PRP preparation kits and MSC-derived exosomes serve different logistical and biological roles, and they are not mutually exclusive procurement decisions. ExaVeyra supplies cGMP-manufactured MSC-derived exosome material to NPI-verified practices nationwide, and is preparing a PRP kit line for licensed practices.
For practices documenting the topical application step, details of the CuraCator applicator are on the manufacturer's site: curacator.com
The Regulatory Picture for Each
Understanding the regulatory status of both products is a non-negotiable part of responsible clinical procurement. The following is a factual description of the current regulatory landscape, not legal advice.
PRP is a blood component, so it falls outside FDA’s HCT/P framework at 21 CFR 1271.3(d)(2). The devices used to prepare it, including centrifuges and disposable kits, are regulated as medical devices, and many hold FDA 510(k) clearance for specific intended uses. PRP is not an FDA-approved drug, and practitioners should not make drug-like efficacy claims when using or marketing PRP services.
MSC-derived exosomes present a more complex regulatory profile. Exosomes are secreted cell products that fall outside the HCT/P definition at 21 CFR 1271.3(d)(3), so the section 361 pathway does not apply. FDA regulates exosome products intended to treat diseases or conditions as drugs and biological products, which require an IND for clinical investigation and a BLA for marketing. There are no FDA-approved exosome products for general clinical use in the United States as of the date of this article. The FDA’s 2019 public safety notification on exosome products sets out that position, and the agency continues to watch this category closely. Practitioners using exosome products in clinical protocols should consult qualified regulatory and legal counsel before doing so.
For practitioners in B2B procurement, the relevant question is whether the supplier provides the manufacturer's facility registration and full quality documentation for each lot. Exosome manufacturers are separate from compounding pharmacies; our explainer on 503A vs 503B compounding covers how compounded preparations are regulated.
What Practitioners Should Take Away
PRP and MSC-derived exosomes are biologically distinct products with different mechanisms, different regulatory histories, and different practical requirements. Neither is a replacement for the other, and neither is appropriate to market with unsupported therapeutic claims.
PRP is an autologous, growth-factor-rich preparation with a long clinical track record and a familiar regulatory pathway. Its variability is both a practical challenge and, in some contexts, a feature: it reflects the patient's own biology.
MSC-derived exosomes are a newer class of allogeneic biologic with a rapidly expanding research base. Their per-lot characterization is an advantage from a quality documentation standpoint. Their regulatory pathway requires careful attention, and practitioners should not incorporate them into clinical use without appropriate regulatory guidance.
Both are active areas of scientific investigation. Both carry research interest that is scientifically legitimate. Neither has the large-scale Phase 3 evidence base that would support broad clinical efficacy claims. Responsible practitioners communicate this accurately to patients and design protocols within the bounds of current regulatory requirements.
Educational Disclaimer: This article is intended for licensed medical professionals and is for informational and educational purposes only. It does not constitute medical advice, clinical protocol guidance, legal advice, or regulatory guidance. No efficacy claims are made for either MSC-derived exosomes or PRP. Neither product is FDA-approved for the applications described in this article. Practitioners are solely responsible for verifying current regulatory requirements applicable to their clinical use of any biologic product. Consult qualified legal and regulatory counsel before incorporating any biologic product into clinical practice.
Tan F, et al. Clinical applications of stem cell-derived exosomes. Signal Transduction and Targeted Therapy. Jan 2024;9:17. DOI: 10.1038/s41392-023-01704-0.
View source 1Chen Y, et al. Exosome Source Matters: A Comprehensive Review from the Perspective of Diverse Cellular Origins. Pharmaceutics. Feb 2025;17(2):147. PMCID: PMC11858990.
View source 2Everts PA, et al. Platelet-Rich Plasma: New Performance Understandings and Therapeutic Considerations in 2020. International Journal of Molecular Sciences. 2020;21(20):7794. PMCID: PMC7589810.
View source 3Mohan S, et al. Clinical Frontiers of Exosome Research: A Comprehensive Analysis of Human Trials. Journal of Pharmacology and Pharmacotherapeutics. 2025;17(2):174-190. DOI: 10.1177/0976500X251361201.
View source 4Roszkowski S. Therapeutic potential of mesenchymal stem cell-derived exosomes for regenerative medicine applications. Clinical and Experimental Medicine. 2024;24(1):46. DOI: 10.1007/s10238-023-01282-z. PMID 38427086.
View source 4bWelsh JA, et al. Minimal information for studies of extracellular vesicles (MISEV2023): From basic to advanced approaches. Journal of Extracellular Vesicles. Feb 2024;13(2):e12404. PMID 38326288. PMCID: PMC10850029.
View source 5Bos JD, Meinardi MM. The 500 Dalton rule for the skin penetration of chemical compounds and drugs. Experimental Dermatology. Jun 2000;9(3):165-9. PMID 10839713. DOI: 10.1034/j.1600-0625.2000.009003165.x.
View source 6Mulcahy LA, Pink RC, Carter DRF. Routes and mechanisms of extracellular vesicle uptake. Journal of Extracellular Vesicles. 2014;3:24641. PMID 25143819. PMCID: PMC4122821.
View source 7Souza ILM, Suzukawa AA, Josino R, Marcon BH, Robert AW, Shigunov P, Correa A, Stimamiglio MA. Cellular In Vitro Responses Induced by Human Mesenchymal Stem/Stromal Cell-Derived Extracellular Vesicles Obtained from Suspension Culture. International Journal of Molecular Sciences. Jul 2024;25(14):7605. PMID 39062847. PMCID: PMC11277484. CC BY 4.0.
View source 8What is the main difference between exosomes and PRP?+
PRP is an autologous product prepared from the patient's own blood, containing concentrated platelets and growth factors. MSC-derived exosomes are allogeneic manufactured biologics produced from donor mesenchymal stem cells. They operate through different biological mechanisms and serve different practical roles in a clinical setting.
Is PRP FDA-approved?+
PRP as a substance is not separately FDA-approved as a drug. PRP preparation devices may hold FDA 510(k) clearance. As a blood component, PRP falls outside FDA’s HCT/P framework at 21 CFR 1271.3(d)(2). Practitioners should consult current FDA guidance and legal counsel regarding specific PRP applications.
Are exosomes FDA-approved?+
There are currently no FDA-approved exosome products for general clinical use in the United States. FDA regulates exosome products intended to treat diseases or conditions as drugs and biological products, which require an Investigational New Drug (IND) application for clinical investigation. Practitioners should consult current FDA guidance before incorporating exosomes into clinical protocols.
Can exosomes and PRP be used together?+
Some practitioners explore both in combination protocols. The appropriateness of any combined protocol is a clinical decision that rests entirely with the licensed practitioner and is subject to applicable regulatory requirements for each component.
Which has more clinical evidence, exosomes or PRP?+
PRP has a longer clinical history and a larger body of published human studies. MSC-derived exosomes represent a newer category with a rapidly growing research base, including 49 registered MSC-derived EV trials identified in a 2023 Cytotherapy scoping review, within a wider literature of 90 human exosome trials from all sources (plasma, urine, saliva and stem cells among them) analyzed in a 2025 review. Neither has the depth of Phase 3 randomized controlled trial evidence that would support broad efficacy claims across all applications.