Regulatory Notice: This article is written for licensed healthcare practitioners and is intended as a practitioner education resource, not medical advice. PRP is an autologous blood-derived product subject to federal and state regulations. Clinicians are responsible for verifying the regulatory status of any device or product in their jurisdiction and should consult qualified legal or regulatory counsel before adoption.
Platelet-rich plasma has become one of the most widely used autologous biologics in regenerative medicine, with applications spanning orthopedics, sports medicine, dermatology, and aesthetic practice. Yet among the most consequential decisions a clinic makes when adopting PRP is selecting the preparation system. Not all kits produce equivalent platelet concentrations, leukocyte profiles, or growth factor yields. The variability across commercially available systems is well documented in the literature, and understanding the parameters that drive that variability is the starting point for any rigorous procurement process.2
This guide covers the core technical and regulatory considerations practitioners should evaluate before selecting a PRP kit supplier. It is not an endorsement of any specific product or manufacturer.
How PRP Works: Platelet Biology and Growth Factor Release
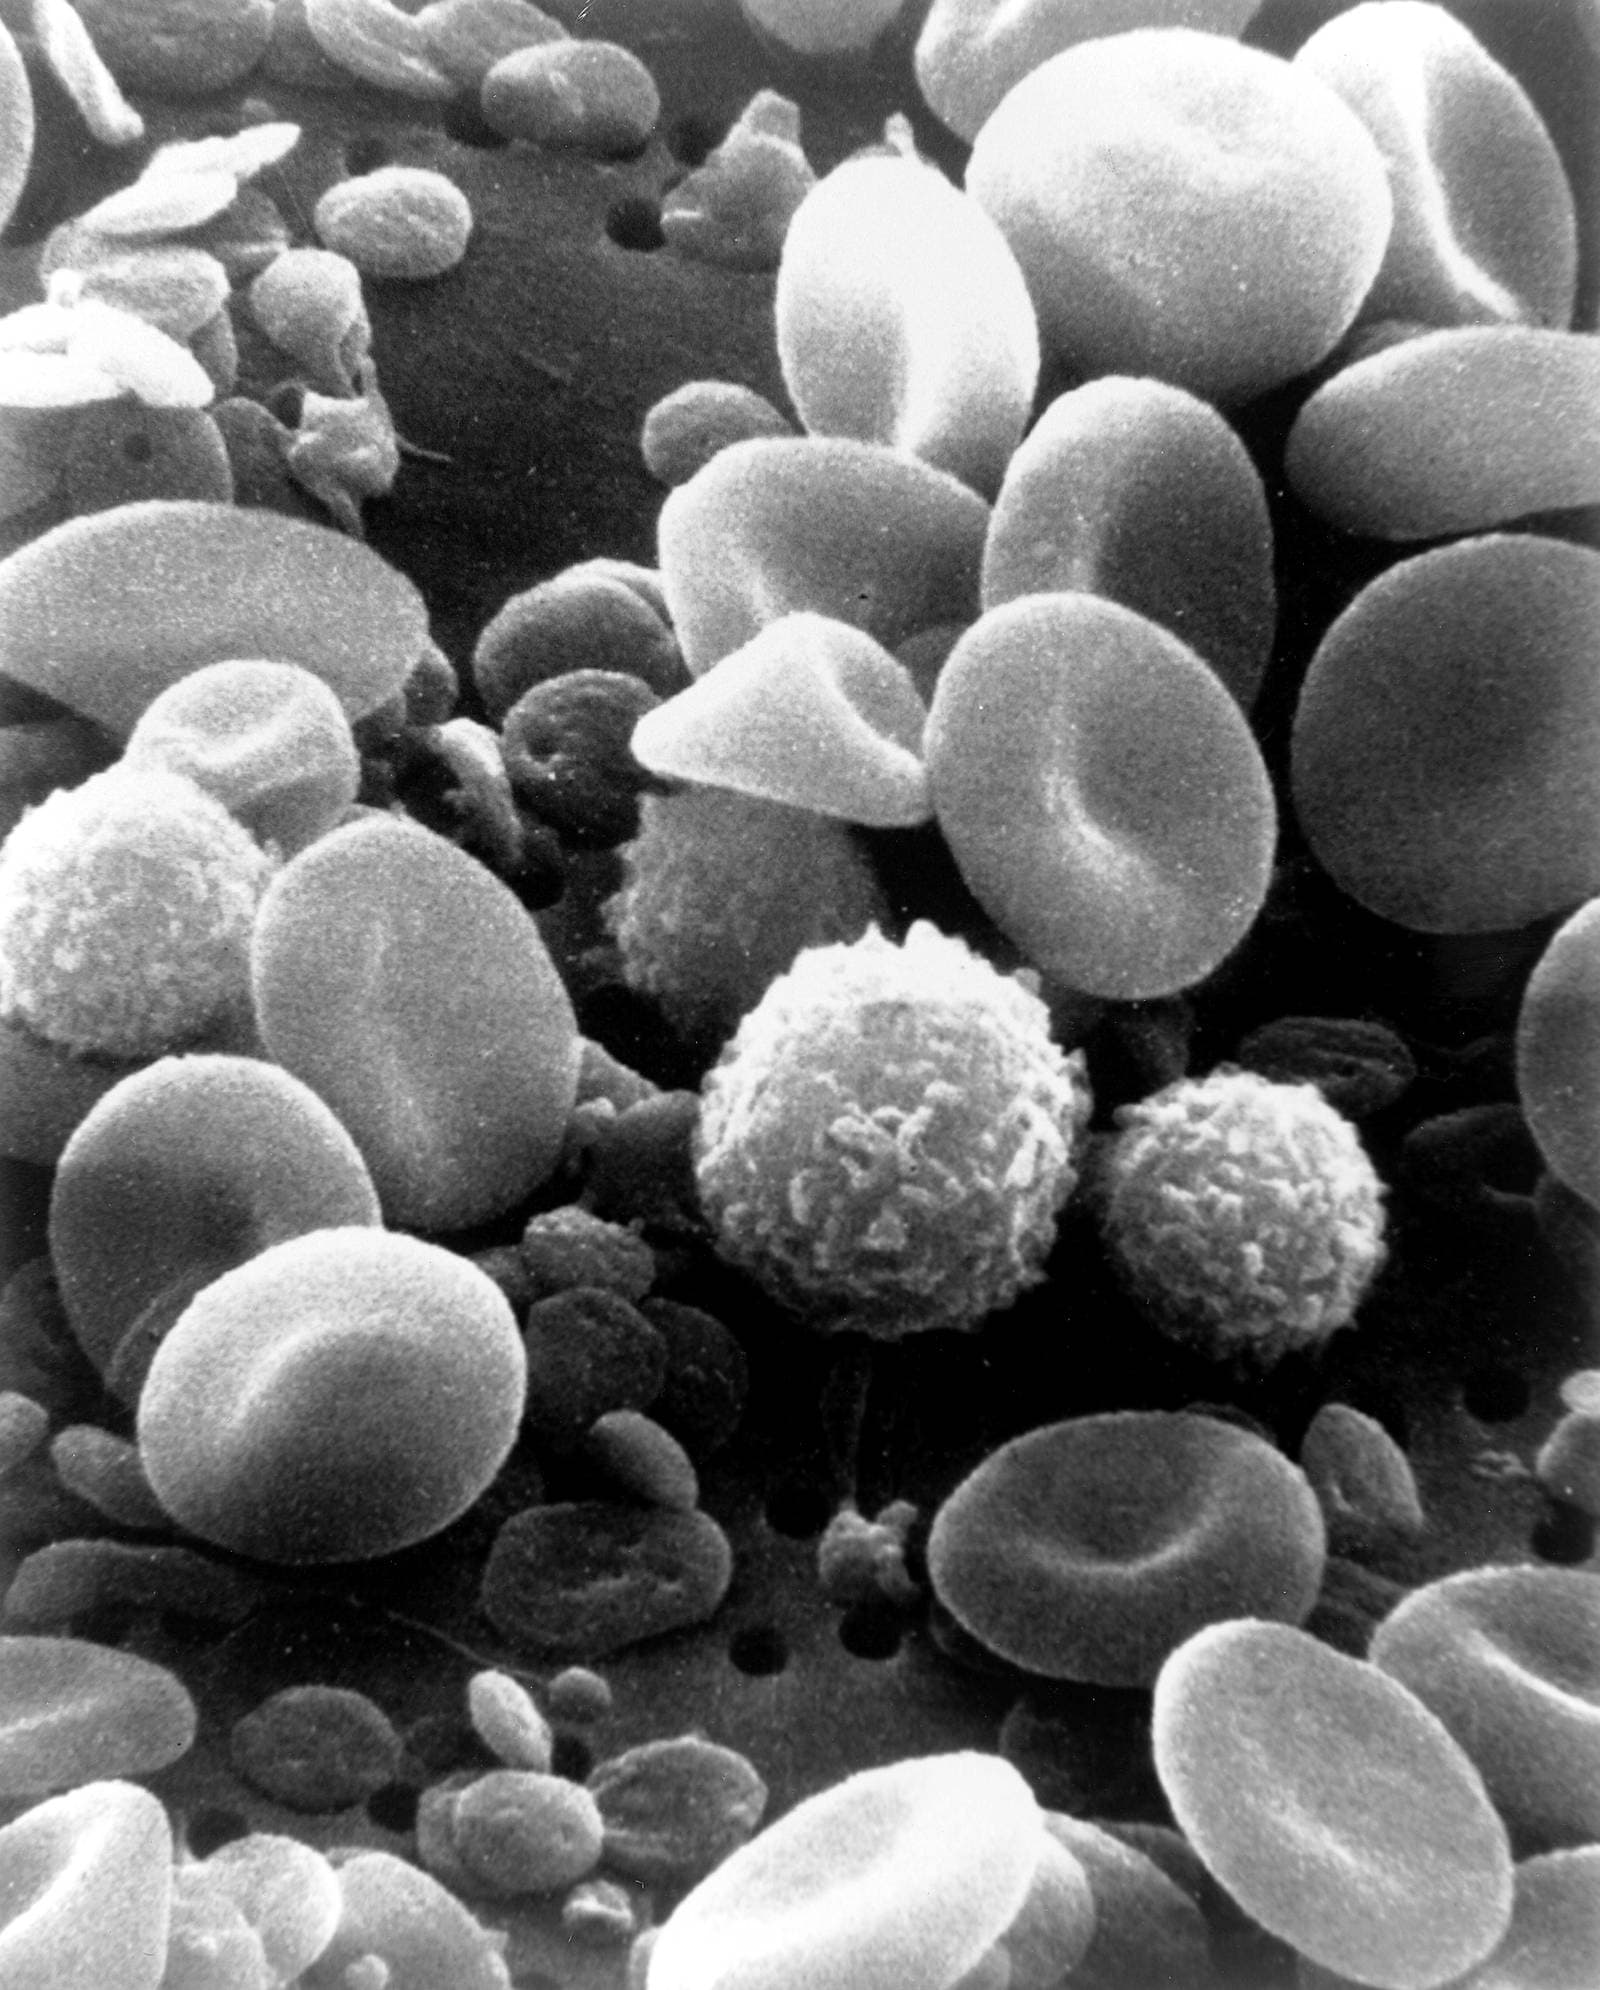
PRP is an autologous concentrate of platelets in a small plasma volume, prepared from the patient's own whole blood (Fig. 1). When activated, platelets degranulate and release a range of bioactive molecules stored in alpha granules, including platelet-derived growth factor (PDGF), transforming growth factor beta (TGF-beta), vascular endothelial growth factor (VEGF), epidermal growth factor (EGF), and insulin-like growth factor 1 (IGF-1). These molecules participate in signaling pathways associated with cell migration, proliferation, angiogenesis, and extracellular matrix remodeling.2
The clinical relevance of these signaling properties is the subject of ongoing research across multiple specialties. Results from published trials are mixed and context-dependent, with variation in outcomes attributable in part to differences in preparation protocols, platelet concentration, and activation methods. Understanding how preparation variables influence the final product is therefore central to any evidence-based kit evaluation.3
Key Variables in PRP Kit Performance
PRP kits differ across several dimensions that directly influence the composition of the final concentrate. Evaluating a kit requires understanding how each variable is controlled and what the manufacturer's published data show.
Centrifuge Speed and Duration
Single-spin protocols separate plasma from red blood cells but may leave the buffy coat poorly defined. Double-spin protocols add a second centrifugation step to concentrate platelets further. Speed (rpm or RCF) and duration interact to determine platelet recovery and leukocyte carry-over (Fig. 2).
Platelet Concentration
The ratio of concentrated platelets to baseline whole blood platelet count is a key output metric. Published literature often targets a 4x to 7x concentration relative to baseline, though optimal thresholds vary by application area and remain under investigation.
Anticoagulant Type
ACD-A (acid citrate dextrose) and sodium citrate are the most common anticoagulants used in PRP tubes. Each affects the pH of the final concentrate and may influence growth factor bioactivity. Heparin is generally avoided due to its inhibitory effects on platelet aggregation.
Leukocyte Inclusion
Leukocyte-rich PRP (L-PRP) retains white blood cells from the buffy coat, while pure or leukocyte-poor PRP (P-PRP) minimizes white cell content. Both are used clinically, with practitioner and protocol considerations influencing the choice.

PRP Classification Systems
Several classification frameworks have been proposed in the academic literature to standardize how PRP products are described and compared across studies. The most commonly referenced systems classify PRP by leukocyte content (present or absent), fibrin network characteristics, and whether an exogenous activator is used.
The PAW (Platelets, Activation, White cells) classification and the DEPA (Dose of injected platelets, Efficiency of production, Purity of the concentrate, Activation used) system each attempt to provide a shared vocabulary for comparing preparations across clinical settings. Neither system has achieved universal adoption, and most kit manufacturers do not explicitly align their labeling to a single classification framework.
For practical purchasing decisions, classification frameworks are most useful as a lens for evaluating published efficacy literature. When a published study describes outcomes with "L-PRP at 5x baseline concentration prepared by double-spin protocol," that description maps onto specific kit parameters a clinic can seek to match or deviate from intentionally.3
Activation Methods: Calcium Chloride, Thrombin, and Autologous Clotting
PRP can be delivered in its liquid (anticoagulated) form for injection, or activated prior to use to accelerate platelet degranulation and fibrin network formation (Fig. 3). The two main exogenous activators are calcium chloride (CaCl2) and bovine thrombin. Some practitioners also use autologous thrombin derived from the patient's own plasma as an alternative to bovine-derived products.
Bovine thrombin carries a historical regulatory concern around immunogenicity and potential antibody formation, which contributed to its decline in favor of calcium-based activation. Autologous thrombin avoids xenogenic material exposure but requires an additional preparation step. The clinical significance of activation method choice is an ongoing area of investigation, with no consensus on superiority in most application contexts.
A clinically important note: not all PRP applications require pre-activation. Many practitioners deliver anticoagulated PRP directly into tissue, where endogenous collagen and tissue factor initiate platelet activation in situ. Kit specifications should be evaluated in the context of the specific protocol the clinic intends to use.
Closed vs Open Systems: Contamination Risk and Documentation
- Processing occurs in sealed tubes throughout
- No manual transfer between vessels
- Reduces contamination exposure risk
- Simplifies sterile handling documentation
- Simplifies aseptic-technique documentation for the device’s cleared use
- May involve open vessels or pipette transfers
- Greater flexibility in custom protocol design
- Higher contamination management requirements
- More complex documentation burden
- Requires rigorous aseptic technique protocols
For most clinic settings, closed systems are the practical default. They are easier to standardize, easier to train staff on, and impose fewer procedural requirements for maintaining sterility. Open systems are more common in academic and research settings where protocol flexibility is a priority.
Regulatory Considerations for In-Office PRP
PRP is a blood component, so it falls outside FDA’s HCT/P framework at 21 CFR 1271.3(d)(2). The devices used to prepare it, including centrifuges and disposable kits, are regulated as medical devices, and many hold FDA 510(k) clearance for specific intended uses. Practitioners should confirm the cleared indications of the specific device they use.
The PRP preparation device (the kit or centrifuge system) is regulated separately from the PRP product itself. Devices used to prepare PRP for in-office use may carry FDA 510(k) clearance for specific indicated uses. Some clearances cover orthopedic applications; others are cleared specifically for wound care or surgical use. Clearance does not extend across all potential application areas, and clinicians are responsible for understanding whether the cleared intended use of a device aligns with their practice.4
Clinicians should also be aware that FDA has issued warning letters to practitioners and manufacturers making unsubstantiated efficacy claims about PRP. Documentation of practitioner decision-making, including literature references, patient selection rationale, and informed consent, is a standard-of-care expectation regardless of regulatory framework.
Supplier Due Diligence Checklist
When evaluating a PRP kit supplier, the following documentation requests are reasonable starting points for due diligence. This list is not exhaustive and does not constitute legal or regulatory advice.
Request the 510(k) clearance number and intended use statement for the kit. Verify independently via the FDA 510(k) database at accessdata.fda.gov. Confirm the cleared intended use matches your practice application.
Request published or internally generated data showing platelet concentration outputs relative to baseline whole blood counts. Manufacturer claims should be verifiable and ideally corroborated by independent laboratory data rather than internal testing alone.
Confirm the type, concentration, and volume of anticoagulant used in the tube. Request biocompatibility and compatibility testing data if additives are included beyond standard anticoagulants.
Request sterility testing certificates for tube materials and activation components. If bovine-derived materials are present (e.g., bovine thrombin), request BSE/TSE documentation.
Confirm the supplier maintains lot-level traceability and can provide documentation linking each product shipment to its manufacturing batch records. This is relevant for both quality management and potential adverse event reporting.
Orthopedic and Sports Medicine Kits Reward a Closer Look at Their Chemistry
Practices preparing PRP for injection in orthopedic and sports medicine settings meet every variable above in its strictest form. The same whole blood volume can yield preparations that differ by orders of magnitude in platelet count, leukocyte content and growth factor release. A 2025 systematic review and network meta-analysis documented this variability across preparation methods, platelet concentrations and dosing regimens.6
A Sealed Draw-Up Port Keeps the Closed System Intact
A closed-system kit combines a collection tube with anticoagulant, a separator gel and a draw-up port. The port lets the clinician extract the platelet-rich layer without breaking the tube seal.
Open transfers expose plasma to ambient air and widen operator-driven variance.
ACD-A Preserves Platelets Through Its Citrate and Dextrose Chemistry
Acid Citrate Dextrose Solution A (ACD-A) is a balanced solution of citric acid, sodium citrate and dextrose. Citrate chelates calcium ions and blocks the calcium-dependent coagulation cascade. Dextrose supplies the metabolic substrate that keeps platelets viable through processing.
Platelets stay inactive until the clinician adds calcium chloride or until they meet subendothelial collagen at the injection site. Sodium citrate alone anticoagulates without the dextrose substrate, and heparin can interfere with aggregation and growth factor release.
Paired with a separator gel and proper centrifugation, ACD-A yields PRP with more intact growth factors that have not been activated prematurely. These include PDGF, TGF-beta, VEGF and EGF.
An Inert, Calibrated Gel Separator Gives the Cleanest Plasma Fraction
The separator gel is a polyester or silica-based material with a specific gravity calibrated to settle between the red cell and plasma layers. After centrifugation it forms a stable barrier, so the plasma fraction can be drawn off cleanly.
A medical-grade gel stays inert, so it should not activate platelets early, absorb growth factors or add contaminants. A poorly designed gel lets red cells into the plasma layer, adding hemoglobin and free heme, which are associated with pro-inflammatory effects at injection sites.
Documented RCF, Spin Time and Spin Count Make Platelet Yield Predictable
Relative centrifugal force (RCF, in g), spin duration and spin count drive final platelet concentration, leukocyte content and growth factor release. A typical single-spin protocol runs at about 1500 to 1900 g for 5 to 10 minutes, depending on the kit and centrifuge.
As one documented example, the Fidia RICHPLAT ORTHO closed-system kit produces 8 mL of PRP at 2.3 times baseline concentration from an 18 mL whole blood draw. It uses a one-touch centrifugation protocol.7
Double-spin protocols add a second step that concentrates platelets further, with longer processing and more handling. The 2025 network meta-analysis found that the number of injections influenced reported results, so a documented, repeatable preparation protocol becomes a purchasing question.6
A Validated Draw-Up Technique Makes Leukocyte Content Reproducible
Leukocyte-poor PRP (LP-PRP, the P-PRP described above) holds fewer white cells than whole blood baseline, while leukocyte-rich PRP (LR-PRP) holds more. Most leukocytes sit in the buffy coat, so the draw-up technique sets the leukocyte content of the final preparation.
A 2025 narrative review of 40 studies published between 2013 and March 2025 compared leukocyte-poor and leukocyte-rich preparations as distinct products. Elevated leukocyte counts carry pro-inflammatory cytokines such as IL-1β and TNF-α to the injection site.5
Closed-system kits with validated draw-up protocols deliver more reproducible leukocyte content than open systems. Asking which type a kit produces at its recommended technique settles the question before purchase.
Seven Documents Complete an Orthopedic Kit Review
Validated Closed-System Workflow
Confirm the kit stays closed from blood draw through final preparation with no open-tube transfers, and request the validated workflow.
Anticoagulant Source
Confirm the ACD-A type, the volume per tube and the solution manufacturer. Citra Labs ACD-A is a commonly referenced standard.
Gel Separator Specification
Confirm the gel material, polyester or silica, its specific gravity and the centrifugation parameters validated for clean separation.
Centrifugation Protocol and Yield
Confirm the recommended RCF, spin duration and spin count, plus the documented platelet recovery and concentration factor at that protocol.
Leukocyte Content
Ask whether the kit produces LP-PRP or LR-PRP at the recommended draw-up technique, with leukocyte concentration stated against whole blood baseline.
Centrifuge Compatibility
Check RCF capability, swing-out or fixed-angle rotor and tube format against the centrifuge already in the practice.
Sterility and Marking
Confirm single-use sterility with lot numbers and expiration dating, plus CE marking or FDA 510(k) clearance as applicable.
PRP and Exosome-Based Biologics: Complementary Research Directions
As practitioners evaluate PRP systems, many are also reviewing emerging research on MSC-derived exosomes as a complementary or alternative approach in certain protocol contexts. Unlike PRP, exosomes are manufactured biologics from donor mesenchymal stem cells rather than autologous blood components. They require a different supply chain, regulatory framework, and quality documentation standard.
PRP has a substantially longer clinical track record. Exosomes represent an earlier and more exploratory stage of clinical research. Some practitioners report using both in combination protocols, though the research supporting such combinations is limited and largely preclinical. Clinicians considering either approach should review the available literature in their specific application area and consult with qualified legal and regulatory advisors.1
For an overview of how exosomes and PRP differ in hair restoration research specifically, see our related article: Exosomes for Hair Restoration: What the Research Says.
Frequently Asked Questions
References
- Alves R, Grimalt R. A Review of Platelet-Rich Plasma: History, Biology, Mechanism of Action, and Classification. Skin Appendage Disord. 2018;4(1):18-24.
- Pavlovic V, et al. Platelet Rich Plasma: a short overview of certain bioactive components. Open Med (Wars). 2016;11(1):242-247.
- DeLong JM, et al. Platelet-rich plasma: the PAW classification system. Arthroscopy. 2012;28(7):998-1009.
- Mishra A, et al. Sports medicine applications of platelet rich plasma. Curr Pharm Biotechnol. 2012;13(7):1185-1195.
- Glinkowski WM, Gut G, Śladowski D. Platelet-Rich Plasma for Knee Osteoarthritis: A Comprehensive Narrative Review of the Mechanisms, Preparation Protocols, and Clinical Evidence. J Clin Med. 2025;14(11):3983. PMID: 40507744.
- Khalilizad M, Emadian ST, Marzban Abbas Abadi M. Comparative efficacy of different doses of platelet-rich plasma injection in the treatment of knee osteoarthritis: a systematic review and network meta-analysis. J Orthop Surg Res. 2025;20:221. PMID: 40022138.
- Fidia RICHPLAT ORTHO PRP System, data on file.
Disclaimer: This article is for licensed healthcare practitioner education only and does not constitute medical, legal, or regulatory advice. ExaVeyra Sciences is a wholesale supplier of biologics and does not provide clinical guidance. No product described or referenced in this article is FDA-approved for any specific therapeutic use. All clinical decisions are the sole responsibility of the licensed practitioner.
ExaVeyra Sciences is a wholesale supplier of MSC-derived exosome formulations and regenerative biologics based in Miami, FL. Educational content is developed for licensed practitioners and reflects current published research. ExaVeyra Sciences does not provide clinical recommendations.