The Basic Biology of Exosomes
Exosomes are small membrane-bound vesicles secreted by virtually every cell type in the body. They range from 30 to 150 nanometers in diameter, placing them in a size category smaller than most viruses and orders of magnitude smaller than a red blood cell. Their defining biological role is intercellular communication: they carry molecular cargo from the cell that produces them and deliver it to recipient cells, where that cargo can alter gene expression, protein production, and cellular behavior.
The term "exosome" refers specifically to vesicles that form inside the cell through a process involving late endosomes, also called multivesicular bodies (MVBs). When an MVB fuses with the plasma membrane, the internal vesicles are released into the extracellular space as exosomes (Fig. 1). This distinguishes them from microvesicles, which bud directly from the cell surface, and from apoptotic bodies, which are released during cell death. Together, these three populations constitute the broader category of extracellular vesicles (EVs).
In clinical and commercial contexts, "exosome" is often used as a shorthand for the entire small EV fraction. A 2024 review in Signal Transduction and Targeted Therapy describes exosomes as possessing distinct therapeutic advantages over whole cell therapies, noting their non-immunogenicity, non-infusion toxicity, ease of storage, and absence of tumorigenic potential as key properties driving clinical interest.[1]
Exosomes are not waste products. They are active biological messengers carrying proteins, lipids, mRNA, and microRNA from one cell to another.
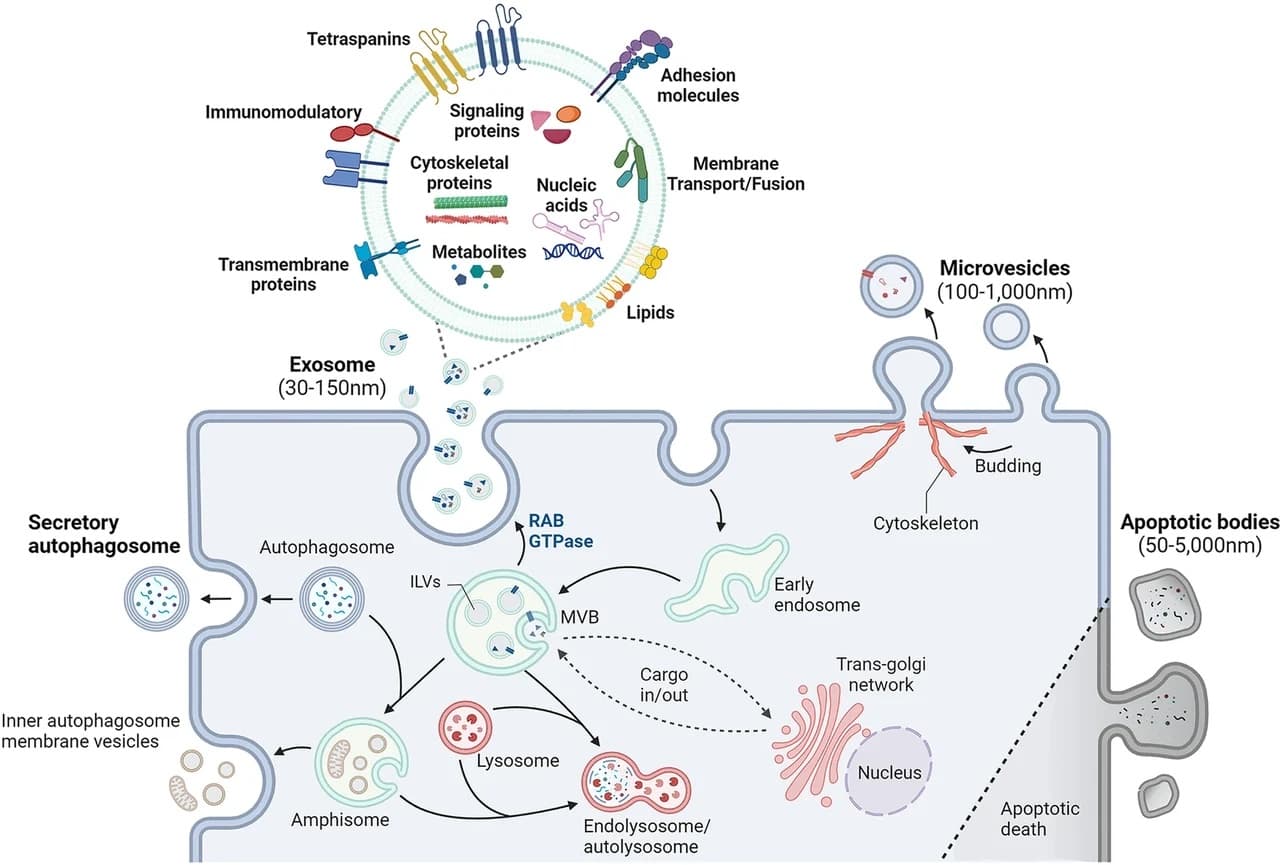
What Exosomes Carry and How They Work
The therapeutic interest in exosomes is inseparable from their cargo. Each vesicle contains a complex mixture of bioactive molecules that varies based on the producing cell type and its physiological state. The primary cargo categories are:
When an exosome reaches a target cell, it can interact through several mechanisms: direct membrane fusion, receptor-ligand binding at the cell surface, or endocytosis followed by intracellular cargo release. Each pathway can produce distinct downstream effects depending on the cell type and the specific cargo delivered.
This multi-pathway signaling capacity is a key reason researchers find exosomes scientifically compelling. Rather than delivering a single drug molecule to a single receptor, an exosome simultaneously delivers a complex biological message that can influence multiple cellular processes.
Source Matters: MSCs and Why They Dominate the Research
Not all exosomes are clinically equivalent. The producing cell type determines the cargo composition, and therefore the biological effects the exosomes are likely to have in a recipient tissue. This principle, articulated clearly in a 2025 review in Pharmaceutics, is one of the most clinically important concepts for practitioners evaluating exosome products.[2]
Mesenchymal stem cells (MSCs) have become the dominant source for exosome research and manufacturing for several reasons. MSCs are well-characterized, ethically accessible (bone marrow, adipose tissue, umbilical cord Wharton's jelly), scalable in culture, and known to produce exosomes with potent anti-inflammatory and immunomodulatory cargo. A 2024 review in Clinical and Experimental Medicine specifically examined MSC-derived exosomes for tissue repair and inflammatory modulation applications, noting bone marrow, adipose, and umbilical cord sources as the most studied.[3]
In a 2023 scoping review in Cytotherapy of 73 registered EV trials, MSCs were the source in 49 (67%). This is not a coincidence. The existing body of MSC biology research provides a mechanistic framework for understanding what their exosomes might do, and a safety track record that supports moving into clinical studies.
The cell source is not a manufacturing detail. It determines the biological identity of the exosome product.
From a procurement standpoint, practitioners evaluating exosome products should always ask: what cell type produced these exosomes, from which tissue, from which donor population, under what culture conditions? These variables meaningfully affect cargo composition and are not interchangeable.
Exosomes vs Whole Stem Cell Therapies
Practitioners coming to exosomes from a stem cell therapy background often ask how these two approaches compare. The distinction matters both clinically and regulatorily.
Whole Stem Cell Therapies
- Living cells that can replicate
- Higher immunogenicity risk with allogeneic sources
- Potential tumorigenic risk requires monitoring
- More complex storage and handling
- Regulatory classification as cell-based biologics
- Longer established clinical track record
MSC-Derived Exosomes
- Acellular, non-replicating vesicles
- Low immunogenicity profile in current research
- Tumorigenicity not reported in the cited reviews
- Frozen storage, scalable manufacturing
- Regulatory classification as biologics or biologics-adjacent
- Rapidly growing clinical evidence base
The 2024 review in Signal Transduction and Targeted Therapy frames exosomes as inheriting the therapeutic effects of their parent cells through the delivery of signaling cargo, while avoiding the risks associated with live cell administration. The review summarizes laboratory and early clinical findings, and it is cited here as a literature summary, not as a claim about any product.[1]
The Current State of Clinical Evidence
A 2025 analysis in the Journal of Pharmacology and Pharmacotherapeutics reviewed 90 published human clinical studies of exosomes, spanning diagnostic, therapeutic and regenerative applications. The authors identify standardised isolation methods, large randomised trials and long-term follow-up as the field’s main open needs.[4]
A 2023 scoping review in Cytotherapy identified 73 registered trials of cell-derived extracellular vesicles, with mesenchymal stromal cells the most common source in 67% of them. A Phase 1b study of AB126, a neural-derived exosome, in acute ischemic stroke is registered on ClinicalTrials.gov (NCT07813130). These registrations show exosome-based products moving through the standard investigational pathway.
For practitioners, the honest characterization is that the evidence base is genuine and growing, but the large-scale, placebo-controlled Phase 3 trials that would support broad efficacy claims across most applications do not yet exist. Most clinical work remains at Phase 1 and Phase 2. That makes exosome science a frontier area, not an established therapy with a thick evidentiary dossier.
Real science. Growing evidence. Early-to-mid stage clinical development. Honest practitioners should communicate all three of these realities to patients.
How to Evaluate an Exosome Product
Quality varies dramatically across the exosome products available to licensed practitioners. Understanding what to look for in a Certificate of Analysis (COA) and what questions to ask a supplier is a core competency for any practice incorporating these biologics.
Regulatory Status in the United States
In the United States, exosome products used to treat diseases and conditions in humans are regulated by the FDA as drugs and biological products, which require an IND for clinical investigation and premarket approval for marketing; the FDA’s 2019 public safety notification states this position and that no exosome product is FDA-approved. Secreted cell factors also fall outside the HCT/P definition at 21 CFR 1271.3(d)(3), so the section 361 pathway does not apply. ExaVeyra supplies exosome material for topical aesthetic use by licensed practitioners, and for laboratory research and clinical research conducted under an IND.
The regulatory landscape for exosomes is actively evolving. The FDA’s 2019 public safety notification states that no exosome product is FDA-approved, and the agency continues to watch this category closely. Practitioners should consult current FDA guidance documents and legal counsel when structuring clinical protocols involving exosome-based products. Staying current with FDA communications on this topic is part of responsible clinical practice in this area.
For B2B procurement, the relevant framework centers on sourcing from manufacturers operating under appropriate FDA oversight, with lot-level documentation. Our 503A vs 503B explainer covers how compounding pathways differ.
What Clinicians Should Take Away
Exosomes are a legitimate and scientifically grounded class of biologics with a growing body of peer-reviewed evidence and an active clinical trial landscape. For practitioners considering them in clinical practice, the following principles apply:
Cell source determines cargo, and cargo determines biology. MSC-derived exosomes have the largest and most rigorous evidence base. Quality documentation matters enormously. The regulatory environment is active and evolving. Efficacy claims should track the actual evidence, which is promising but still maturing.
The practitioners best positioned to integrate these biologics responsibly are those who understand the underlying science, ask hard questions of their suppliers, and communicate honestly with patients about where the evidence currently stands.
Educational Disclaimer: This article is intended for licensed medical professionals and is for informational and educational purposes only. It does not constitute medical advice, clinical protocol guidance, or product endorsement. All citations reference peer-reviewed literature available through PubMed or publisher websites. Regulatory status of exosome products is subject to change; consult current FDA guidance and qualified legal counsel.
Tan F, et al. Clinical applications of stem cell-derived exosomes. Signal Transduction and Targeted Therapy. Jan 2024;9:17. DOI: 10.1038/s41392-023-01704-0.
View source 1Chen Y, et al. Exosome Source Matters: A Comprehensive Review from the Perspective of Diverse Cellular Origins. Pharmaceutics. Feb 2025;17(2):147. PMCID: PMC11858990.
View source 2Roszkowski S. Therapeutic potential of mesenchymal stem cell-derived exosomes for regenerative medicine applications. Clinical and Experimental Medicine. Mar 2024;24(1):46. PMCID: PMC10907468. PMID 38427086.
View source 3Mohan S, et al. Clinical Frontiers of Exosome Research: A Comprehensive Analysis of Human Trials. Journal of Pharmacology and Pharmacotherapeutics. 2025;17(2):174-190. DOI: 10.1177/0976500X251361201.
View source 4What are exosomes?+
Exosomes are small extracellular vesicles, typically 30 to 150 nanometers in diameter, released by virtually all cell types. They carry a cargo of proteins, lipids, messenger RNAs, and microRNAs that reflect the biology of their parent cell. Their primary biological function is intercellular communication.
What is the difference between exosomes and extracellular vesicles?+
Extracellular vesicles (EVs) is the broader category. It includes exosomes (formed inside the cell in endosomes), microvesicles (budded directly from the plasma membrane), and apoptotic bodies. In clinical and commercial contexts, "exosome" is often used loosely to refer to the small EV fraction. Technically precise usage refers to endosomal-origin vesicles in the 30 to 150 nm range.
Why are MSC-derived exosomes used in regenerative medicine?+
Mesenchymal stem cells (MSCs) are known for their anti-inflammatory, immunomodulatory, and tissue-supportive properties. MSC-derived exosomes carry much of this same biological cargo. They offer practical advantages over whole-cell therapies: they are non-replicating, have a favorable safety profile, can be manufactured at scale, and can be stored and shipped frozen.
What is the current regulatory status of exosomes in the United States?+
In the United States, exosome products intended for human use are regulated by the FDA primarily as biologics. The regulatory landscape is actively evolving. Practitioners should consult current FDA guidance and legal counsel when designing clinical protocols involving exosome-based products.
How are exosomes characterized and measured?+
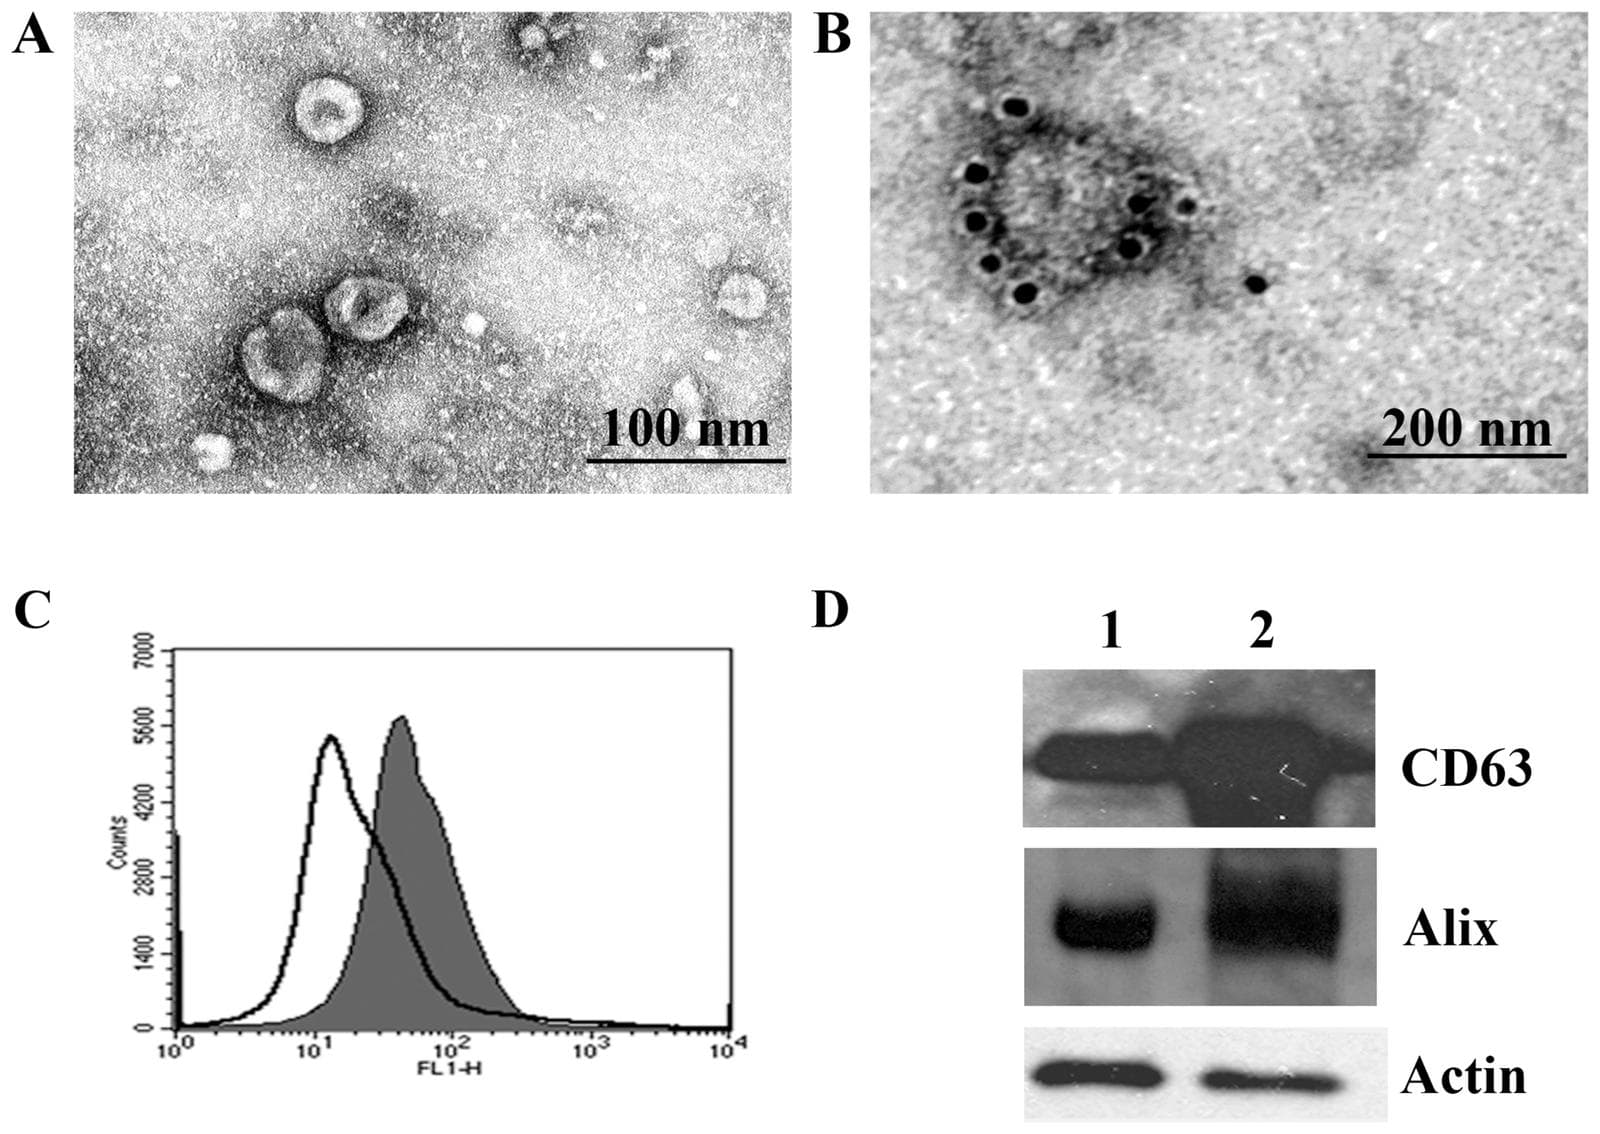
The primary characterization methods are nanoparticle tracking analysis (NTA) for particle concentration and size distribution, transmission electron microscopy (TEM) for morphology, and western blot or flow cytometry for surface marker identification (CD9, CD63, CD81 are standard exosome markers). Reputable suppliers provide this data in a Certificate of Analysis.